Bunkering hose dropped to deck – Incorrect lifting procedure
- Safety Flash
- Published on 23 August 2017
- Generated on 22 November 2026
- IMCA SF 21/17
- 2 minute read
A bunkering hose was dropped to deck from 11 m in the air.
What happened?
A vessel had just completed cargo operations with a supply vessel. The operation had included the transfer onto the vessel of a fuel bunker hose.
In preparation for fuel bunkering operations the vessel rigging crew lifted the hose using the pre-installed hose saddles and lifting slings that were attached.
When the hose was approximately 11 m up, one end of the hose dropped to the deck. No-one was harmed.

What went wrong? What were the causes?
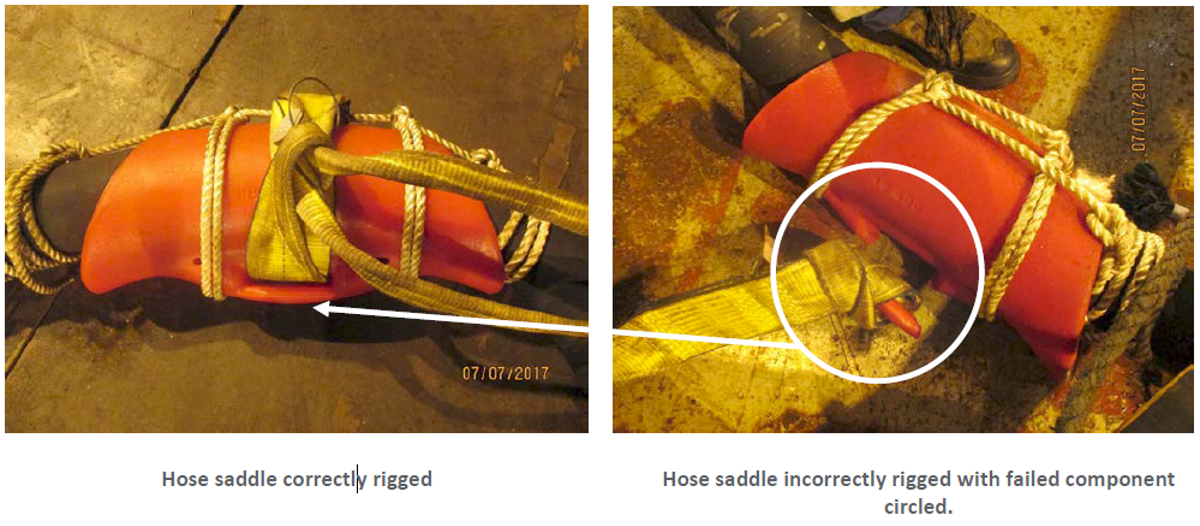
On inspection, it was identified that the lifting sling had been incorrectly installed onto the hose saddle. The sling should have been choked around the saddle and fuel hose but instead, was found choked around the non-load-bearing urethane sling guide.
Although no-one was harmed, and no-one was stood directly under the load, CCTV footage shows the deck crew being in “at risk” positions during the lifting operation and handling the load for no apparent reason.
What lessons were learned? What actions were taken?
- Safe positioning of lifting crew during crane operations – active supervision at all times.
- Thorough inspection – before use – of all pre-rigged lifting equipment coming from external parties.
- Reiteration of the importance and the correct use of lift plans.
- Stop the job when exposed to unfamiliar equipment!
Related safety flashes
-
IMCA SF 08/16
13 April 2016
-
IMCA SF 11/08
23 June 2008
IMCA Safety Flashes summarise key safety matters and incidents, allowing lessons to be more easily learnt for the benefit of the entire offshore industry.
The effectiveness of the IMCA Safety Flash system depends on the industry sharing information and so avoiding repeat incidents. Incidents are classified according to IOGP's Life Saving Rules.
All information is anonymised or sanitised, as appropriate, and warnings for graphic content included where possible.
IMCA makes every effort to ensure both the accuracy and reliability of the information shared, but is not be liable for any guidance and/or recommendation and/or statement herein contained.
The information contained in this document does not fulfil or replace any individual's or Member's legal, regulatory or other duties or obligations in respect of their operations. Individuals and Members remain solely responsible for the safe, lawful and proper conduct of their operations.
Share your safety incidents with IMCA online. Sign-up to receive Safety Flashes straight to your email.